

Mental Health & Chronic Care Apps
CBT modules, adherence tracking and clinician hand-off, built to NICE evidence standards.
Virtual care, remote monitoring, digital therapeutics and AI triage, shipped by senior teams, with the clinical safety case and SaMD evidence pack in the box.

One accountable senior pod owns it end to end: virtual care, safe DTx and remote monitoring at scale.
CBT modules, adherence tracking and clinician hand-off, built to NICE evidence standards.
Wearables and home devices with alerting, escalation and clinician dashboards, HealthKit, Fit and CGM rails.
MHRA SaMD-aligned DTx for mental-health, chronic and post-acute care, evidence pack per release.
EPS, e-RS and US ePA, booking-to-prescription flows cleared through every gateway.
Booking, video, async and prescribing rails, built to NHS Digital, HIPAA and MHRA SaMD standards.
Symptom triage, severity scoring and routing, explainable, audit-trailed, safety-cleared.
Every BritonOne Technology telehealth build ships clinical safety, SaMD evidence and DSPT alignment with the code, not months after launch. Platforms clear SaMD first time and scale from pilot to national without remediation sprints.
Bookings weeks out, postcode lottery for specialists, no async channel.
Patients jot readings in a notebook; clinicians see them weeks late.
Platform, EHR, pharmacy and wearables in four silos, staff retype between them.
SaMD class figured out at submission; evidence retrofitted to claims.
Booking, video, async and prescribing on one surface, nine-minute median wait.
Wearables stream to one timeline; thresholds raise alerts before exacerbation.
Telehealth, EHR, prescribing and wearables share one typed FHIR contract.
Classification opens at architecture; submission is a checkbox, not a project.
Selected work across B2C telehealth, payer virtual care, mental health, chronic disease and digital therapeutics, anonymised where required, specific on the result.
End-to-end telehealth from booking to prescribing for an EU payer covering 18M lives, nine-minute median wait, clinician utilisation up 38%.
MyChart-equivalent member surface with claims-integrated virtual care.
MHRA-aligned CBT modules with clinician hand-off and NICE evidence.
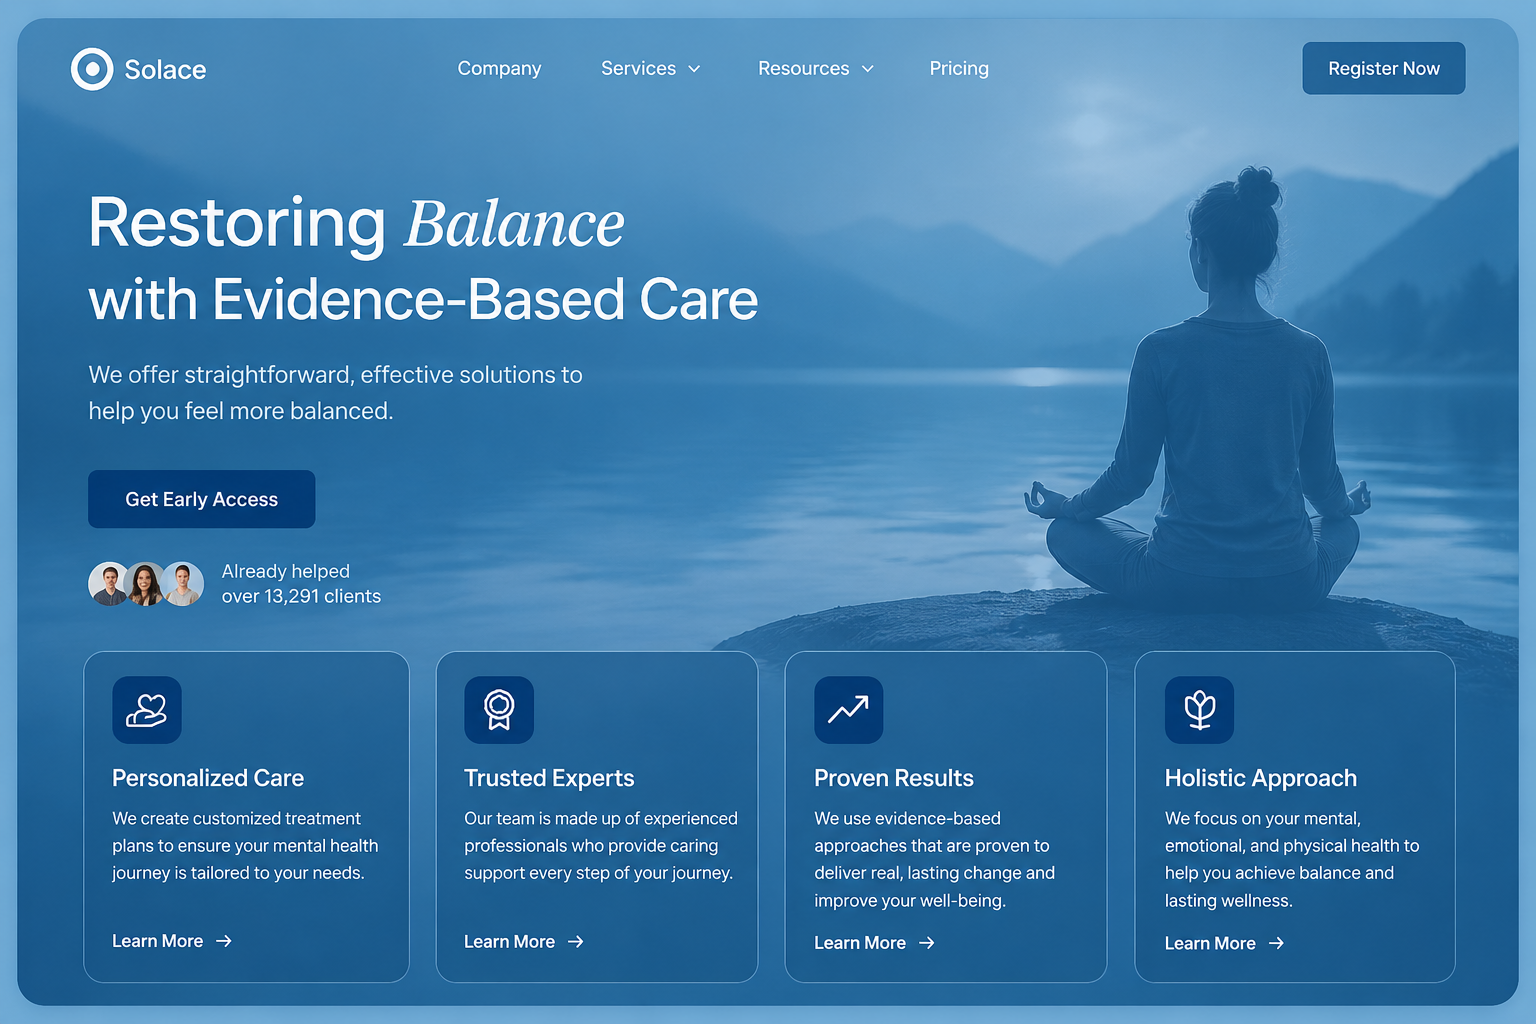
Wearables and BP cuffs streaming to a clinician timeline with alerting.
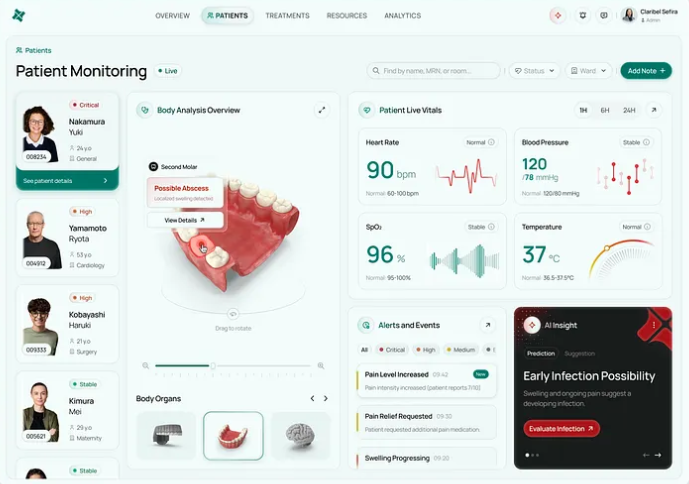
Async image upload, AI triage, and consultant routing across thirty-two GP practices.
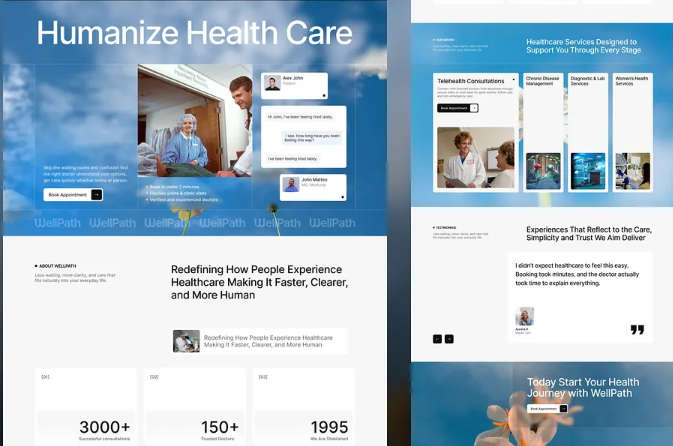
App-led recovery programme with PROMs capture and exercise progression, MHRA SaMD cleared.
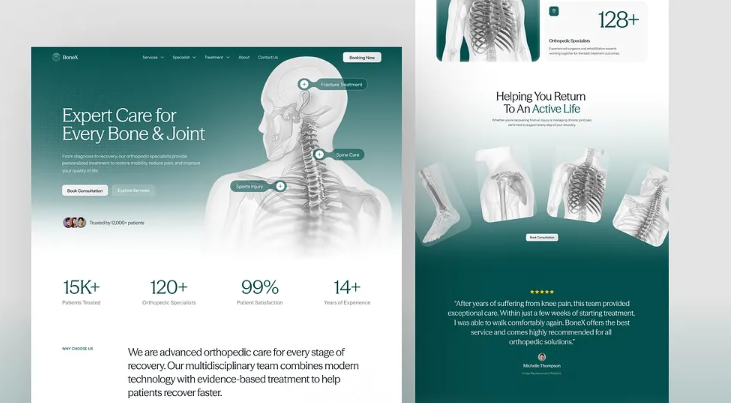
Production integrations across every telehealth estate: video, e-prescribing, wearables and clinical data wired into a single audit-ready surface.
Connected. Unified. Audit-ready.
MHRA / FDA classification opens at architecture. Clinical evaluation, ISO 14971 risk and post-market plans ship with the build.
Typed FHIR profiles bind telehealth, EHR, prescribing and wearables, conformance-tested in CI, changed through PRs.
Wearables, devices, consults and meds collapse into one timeline with thresholds, alerting and per-event audit trail.
Every engagement walks the same path, sized to your problem, but with the same verification gates baked in.

Two-week paid sprint. Architect-led. Output: regulator map, costed roadmap, signed scope.
Pod composition, sequenced milestones, change-control governance, and risk register.

Reference architecture, threat model, design system, and acceptance criteria locked.
Weekly demos, trunk-based, CI/CD from day one. Code reviewed against spec at every gate.

Unit, integration, e2e, security, performance, and accessibility, automated and gated.

Blue-green or canary, observability live before launch, rollback rehearsed.

Managed services or hypercare hand-off. Defined SLOs, named on-call, monthly reviews.
Success stories
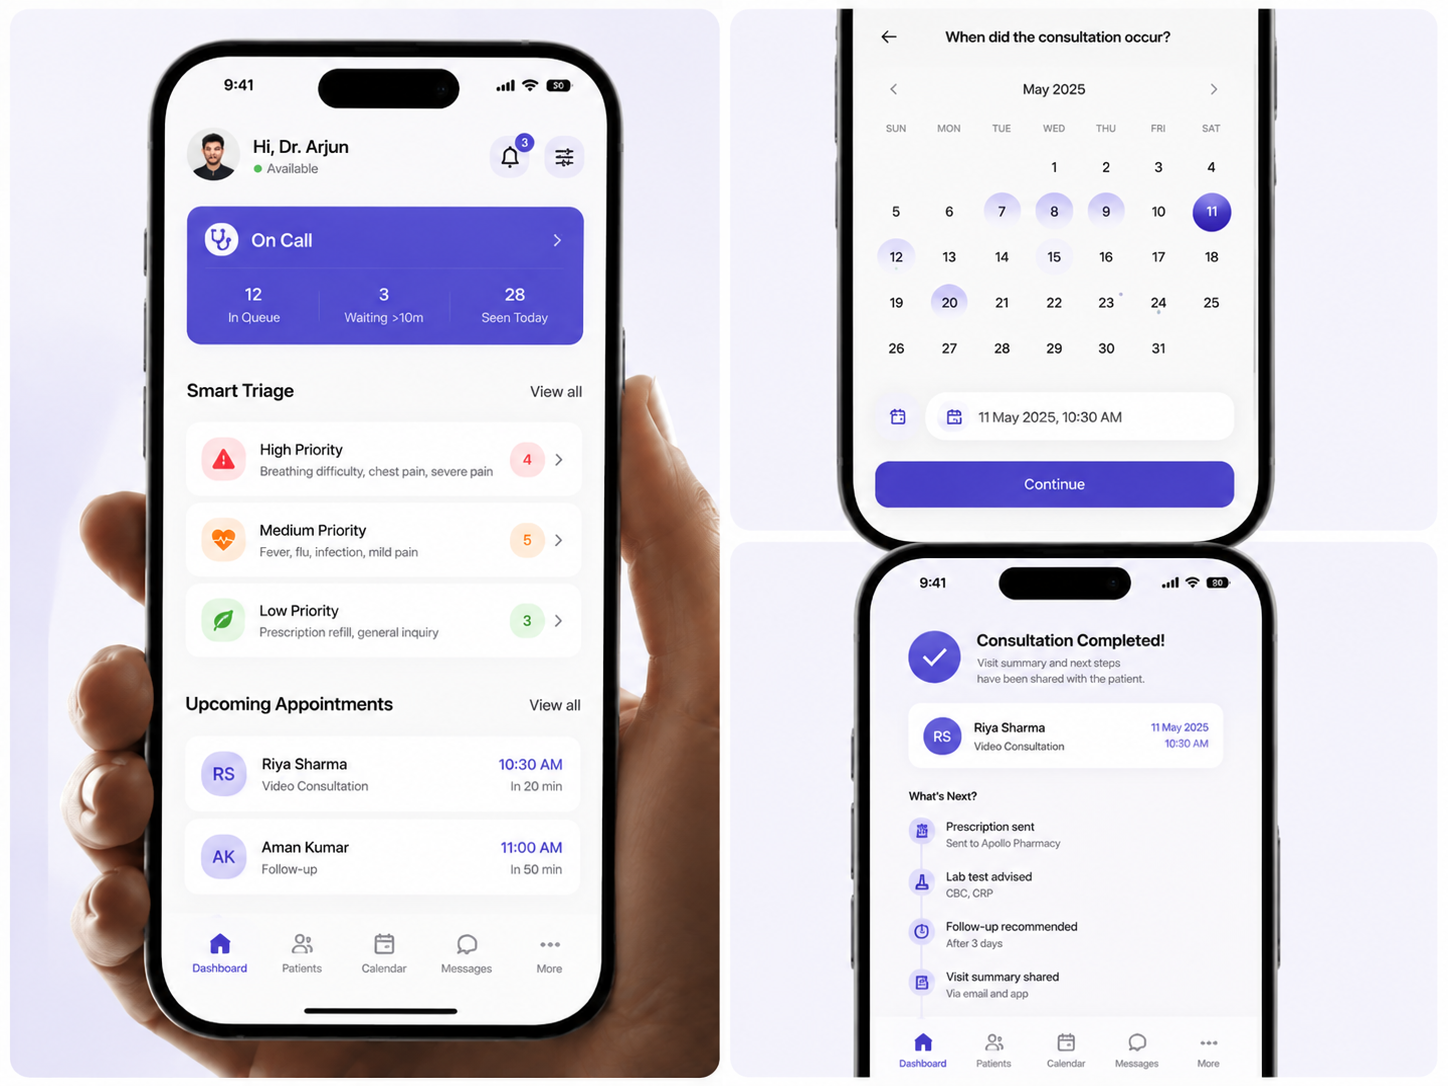
Photo-and-symptom-first triage app cut consultation prep time 54% for a telemedicine provider.
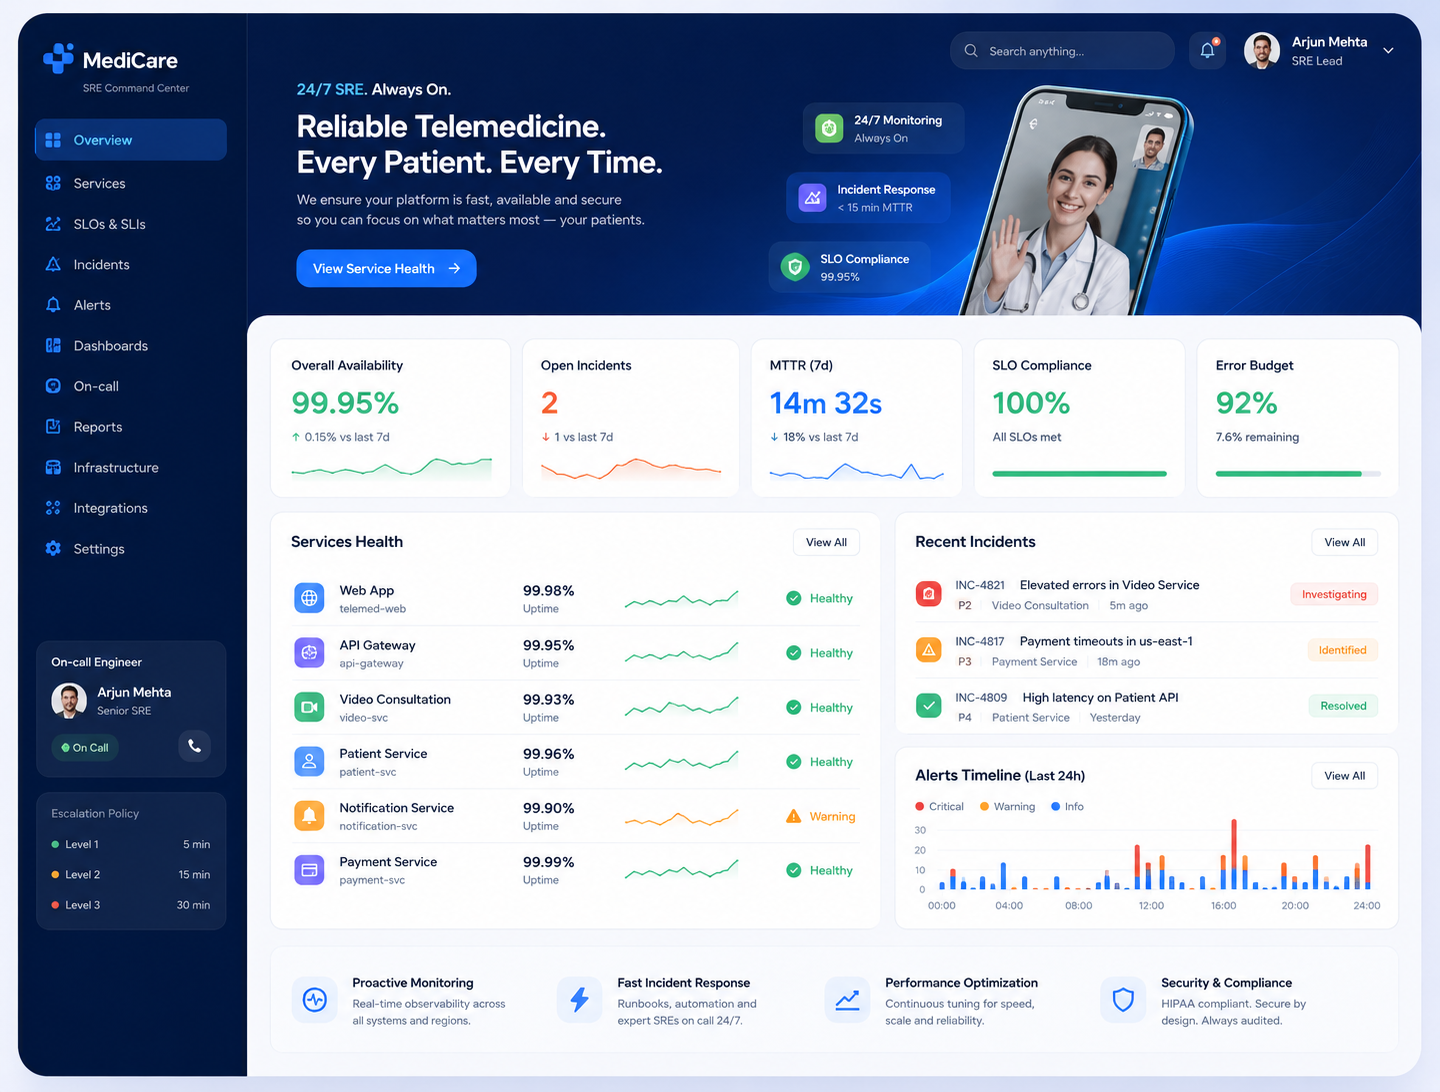
Ran a telemedicine platform to a 99.98% SLO with a follow-the-sun on-call.
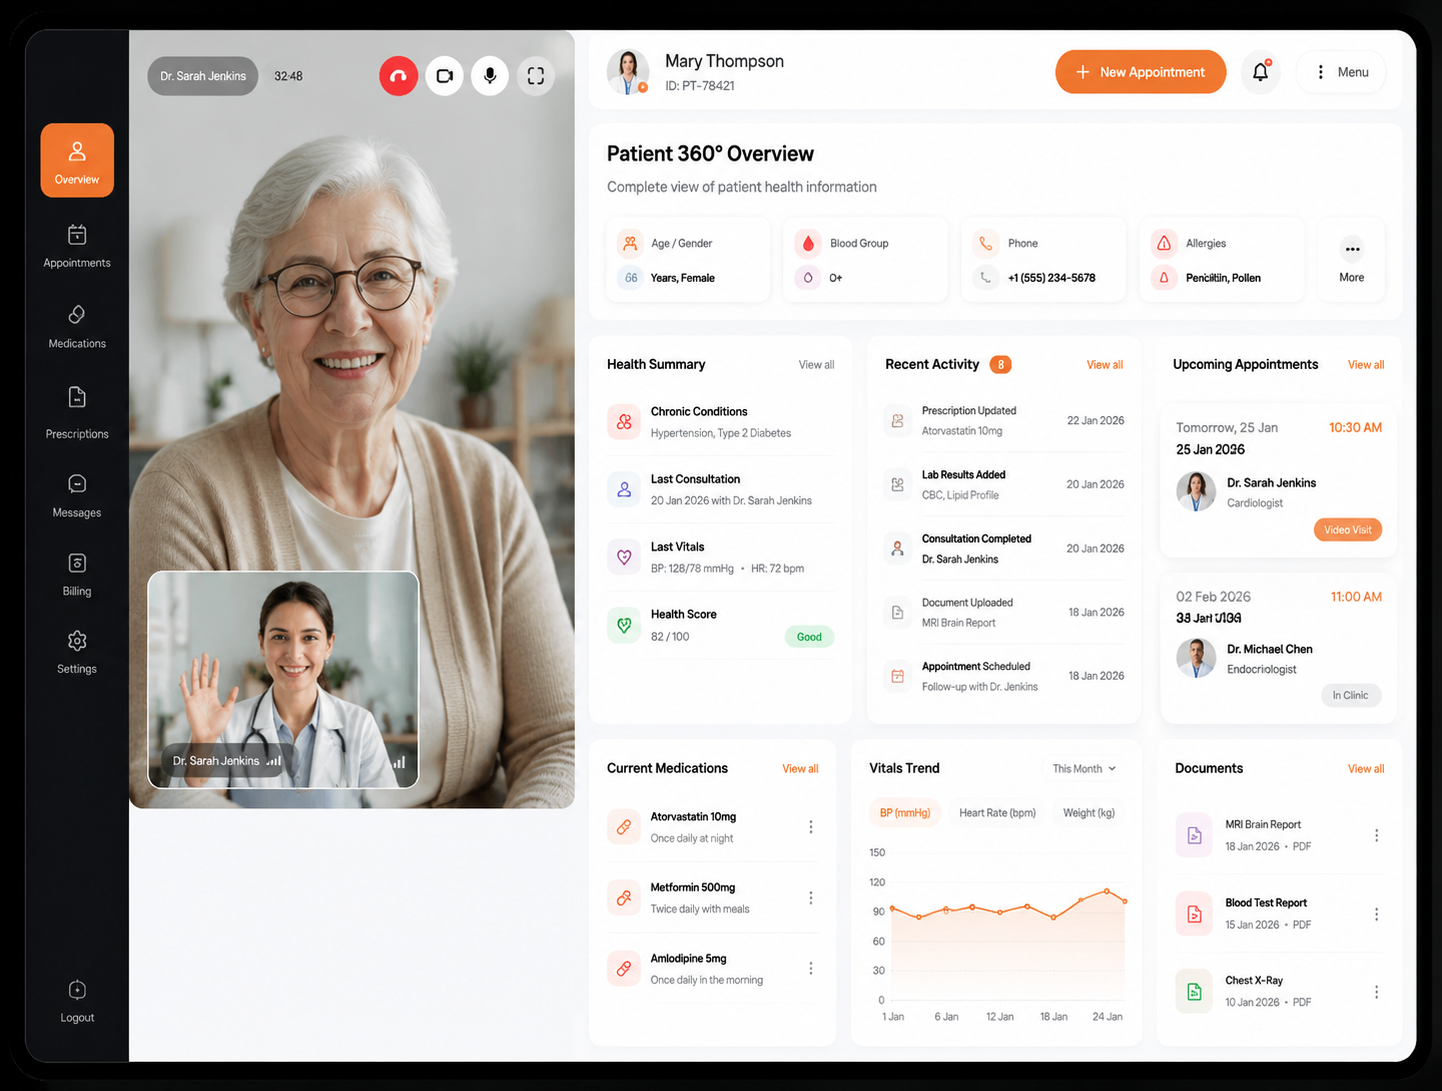
Unified a fragmented patient view, lifting care-team efficiency 24% at a telemedicine provider.
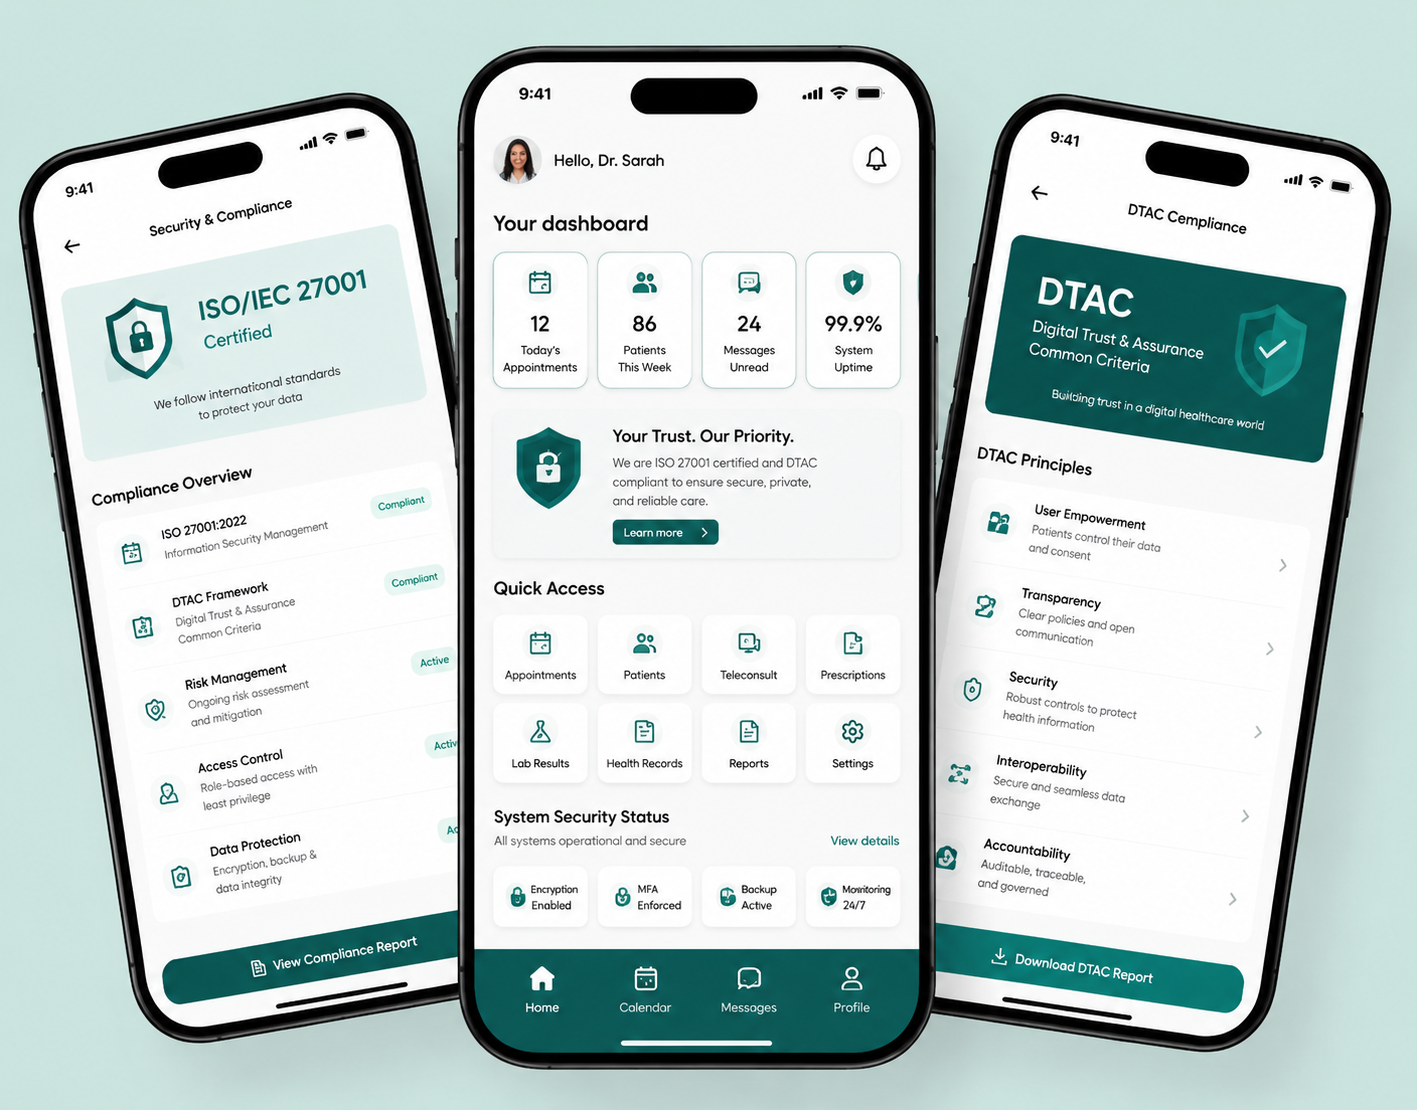
Achieved ISO 27001 and NHS DTAC assurance at first assessment for a telemedicine platform.
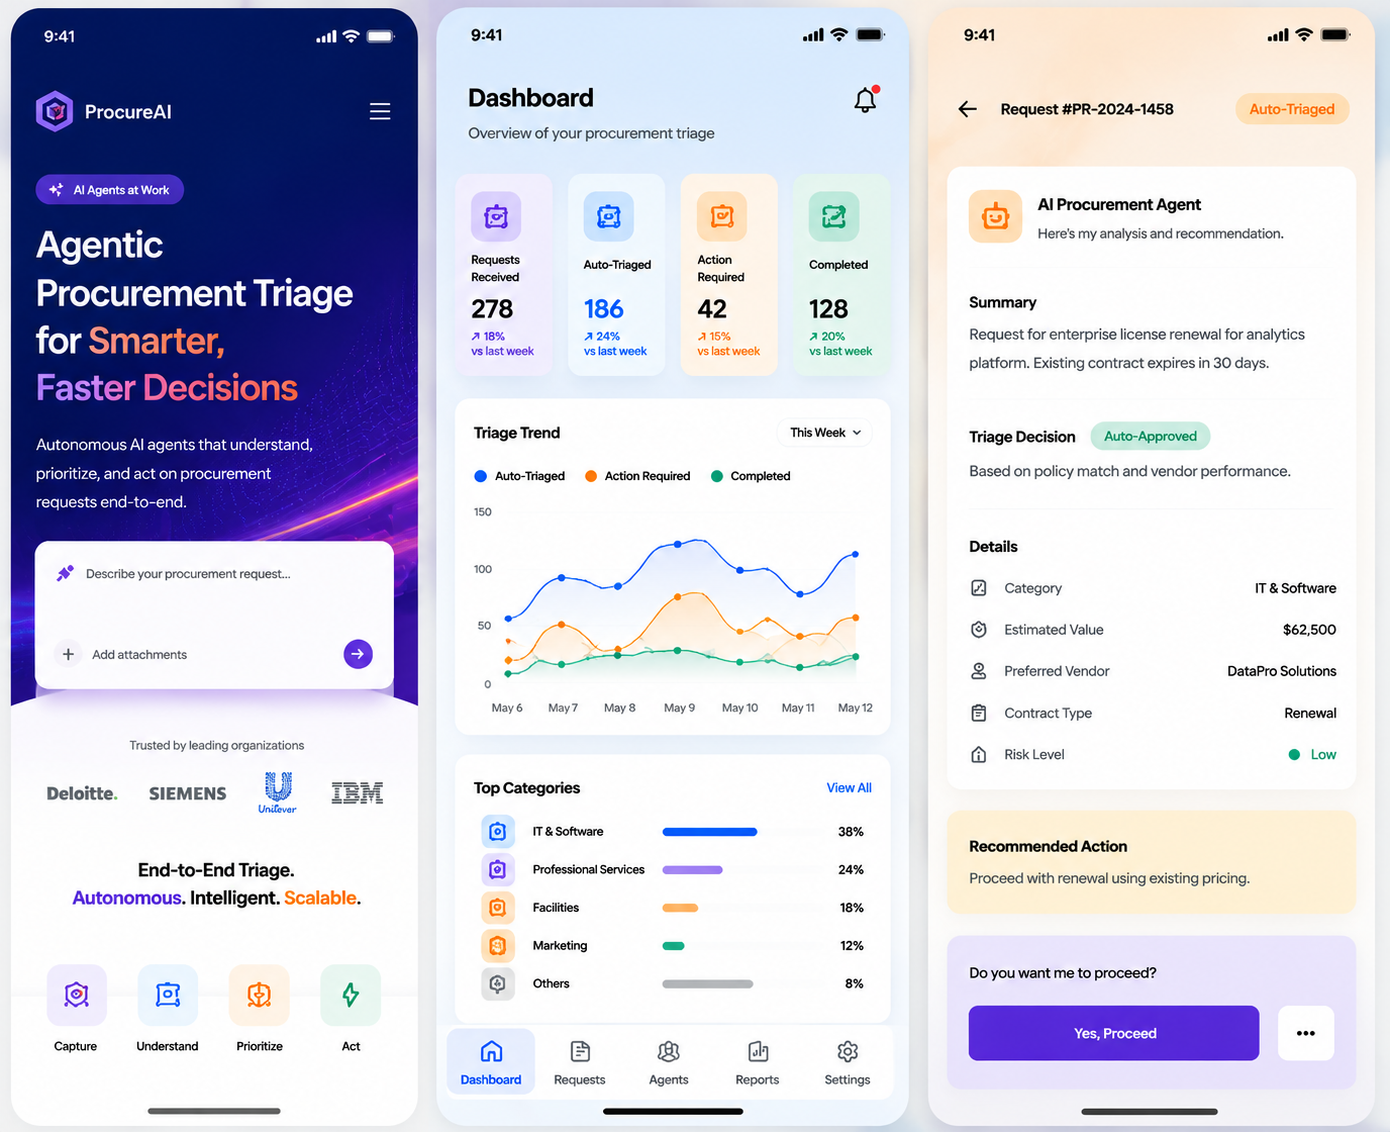
Routed and matched 73% of purchase requests end to end, escalating only genuine exceptions.
Stood up a board-ready AI governance and model-risk framework for a pharma company in 9 weeks, cleared at first internal audit.
Strangled a validated legacy system into microservices, cutting change lead time 40% for a pharma manufacturer.
Migrated 900 clinical workloads off two datacentres to the cloud with zero downtime on patient-facing systems.
Delivered validated, GxP-compliant CI/CD, cutting release lead time 8x with full audit evidence.

Cut monthly cloud spend 37% for a genomics biotech without slowing a single pipeline.
Catalogued and lineage-traced 100% of GxP-regulated data domains for a pharma manufacturer.
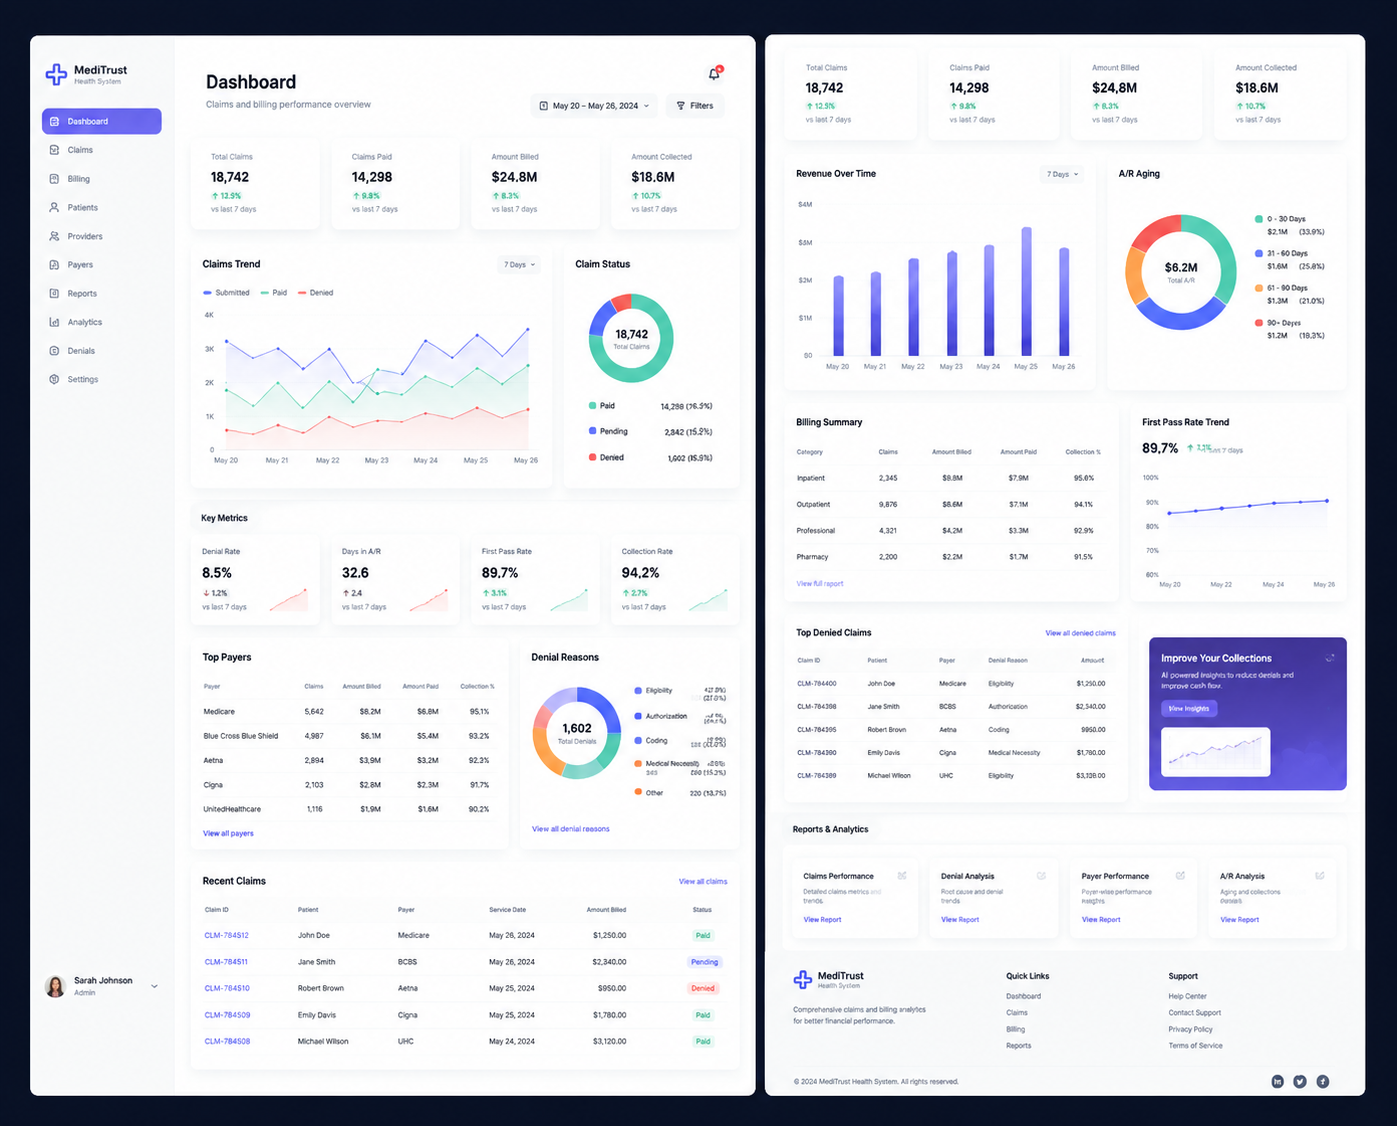
Unified claims and billing data, cutting rejected-claim rework 38% for a hospital group.
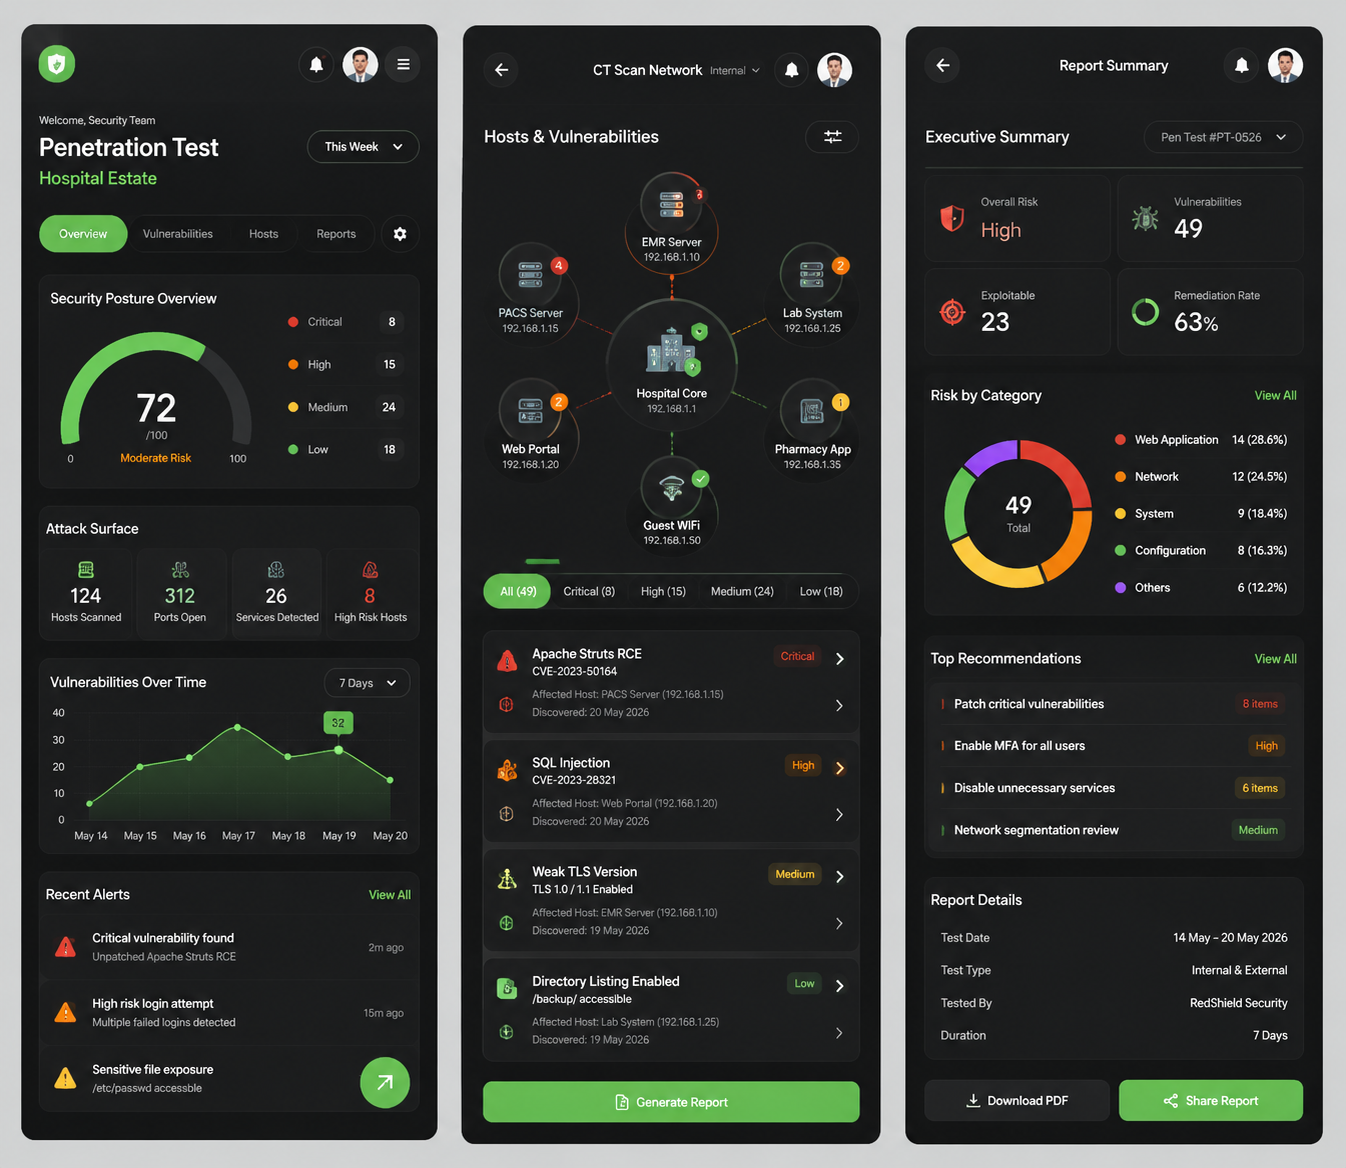
Surfaced 61 exploitable paths across a hospital estate, prioritised by patient-safety impact.
Reached validated Annex 11 compliance for a pharma manufacturer in 12 weeks.

Identified nine design-level risks in a biotech's lab-data platform before build.
Penetration-tested the credential vault and its sync, verifying encryption and access controls end to end so stored secrets stayed protected.
Delivered an audit-ready blockchain architecture for tamper-evident patient records and consent, cleared against HIPAA and GDPR before build.
BritonOne Technology is a full-cycle engineering company that builds and operates production software for regulated estates. Since 2017, we have shipped programmes that clear audit on the first pass across banking, insurance, wealth, healthcare, and biotech. Our teams pair deep domain knowledge with disciplined engineering, treating compliance, security, and resilience as first-class deliverables. From architecture through to live operations, we stay accountable for the systems we build, measuring success by uptime, audit outcomes, and defensible business results.
We don't compete on lowest day-rate. We compete on shipped outcomes inside environments that have to clear audit.

Every engineer on every engagement is at least senior, typically eight to fifteen years deep in their craft. No bench rotations, no junior pyramid hidden behind a glossy proposal, no bait-and-switch after contract signature. The architect who scoped your engagement is the same person committing code by week three.

FCA, PRA, EBA, BaFin, FINMA, HIPAA, SOC 2 Type II: every framework we work under is treated as a design constraint from day one, not a final-stage gate. Evidence trails, model-risk packs, change-control artefacts, and pen-test reports ship alongside the code, ready for second-line review without a remediation sprint.

Small pods of three to seven engineers, each with a named delivery lead who owns scope, schedule, and outcomes from kickoff to hand-off, never a faceless team you have to chase for an answer. Weekly demos run against the signed scope, frequent verification gates catch regressions early, and quarterly outcome reviews measure real progress against the original business case rather than a moving target. Together those rituals catch scope drift before it has any chance to compound, so programmes that should take six months don't quietly stretch into eighteen, budgets stay anchored to what was agreed, and every milestone ships with a written, testable definition of done that both sides sign off before we move on.

We don't disappear the moment the engagement closes. Managed services, hypercare windows, named on-call rotations, or quarterly health checks: pick the depth that matches your operational risk profile. About seventy percent of clients return for a second programme, usually because the team that shipped the first one is still on the other end of the page.
Anonymous under MNDA. Each quote is from a senior telehealth buyer who owned the engagement end to end.
“Their telehealth team understood HIPAA, GDPR, and NHS Digital better than my own compliance team. We launched in six months with no findings.”
Direct answers to what procurement, security, and delivery leads weigh before signing: compliance, integration, and the accountability we put in writing.
SaMD classification opens at architecture, not submission. We work to IEC 62304 software lifecycle, ISO 14971 risk management, and the relevant MHRA / FDA Digital Health guidance. Clinical evaluation, post-market surveillance plans, and the SaMD technical file emit alongside development so the submission is a checkbox.




